
A miscarriage is a pregnancy that stops developing and is lost during early pregnancy. It is unfortunately common, particularly during the first trimester.
Bleeding, cramping or a change in pregnancy symptoms can happen with miscarriage — but these symptoms do not prove that a miscarriage has occurred. Bleeding and pain can also occur in pregnancies that continue normally, and similar symptoms can occur with an ectopic pregnancy.
Ultrasound, your pregnancy dates and sometimes repeat beta-hCG blood tests are used to work out what is happening.
Pregnancy loss can be physically and emotionally difficult. Some women want detailed explanations immediately, while others need time before discussing what happened. Both responses are completely understandable.
This guide explains what symptoms may occur, why early pregnancy loss is more common than loss later in pregnancy, how doctors confirm the diagnosis, the different ways miscarriage can present, and what treatment may involve.
How common is pregnancy loss?
Early pregnancy loss is common. Around 10% of clinically recognised pregnancies end in early pregnancy loss. The true number is likely higher because some pregnancies are lost before a woman knows she is pregnant.
Pregnancy loss is also strongly concentrated toward the beginning of pregnancy. Approximately 80% of pregnancy losses occur during the first trimester.
Pregnancy loss is much more common early
The chance of pregnancy loss generally decreases as pregnancy progresses.
This describes when pregnancy losses occur. It does not mean that an individual pregnant woman has an 80% chance of losing her pregnancy.
Most pregnancy losses occur during the first trimester, when early embryonic development and chromosome-related problems have their greatest effect.
Pregnancy loss after the first trimester is substantially less common and may have different causes that require further evaluation.
Loss later in pregnancy is far less common than first-trimester loss and is assessed differently by the maternity team.
Symptoms of miscarriage
Symptoms vary considerably. Some women develop obvious bleeding and cramping, while a missed miscarriage may cause very few symptoms and may only be discovered during an ultrasound.
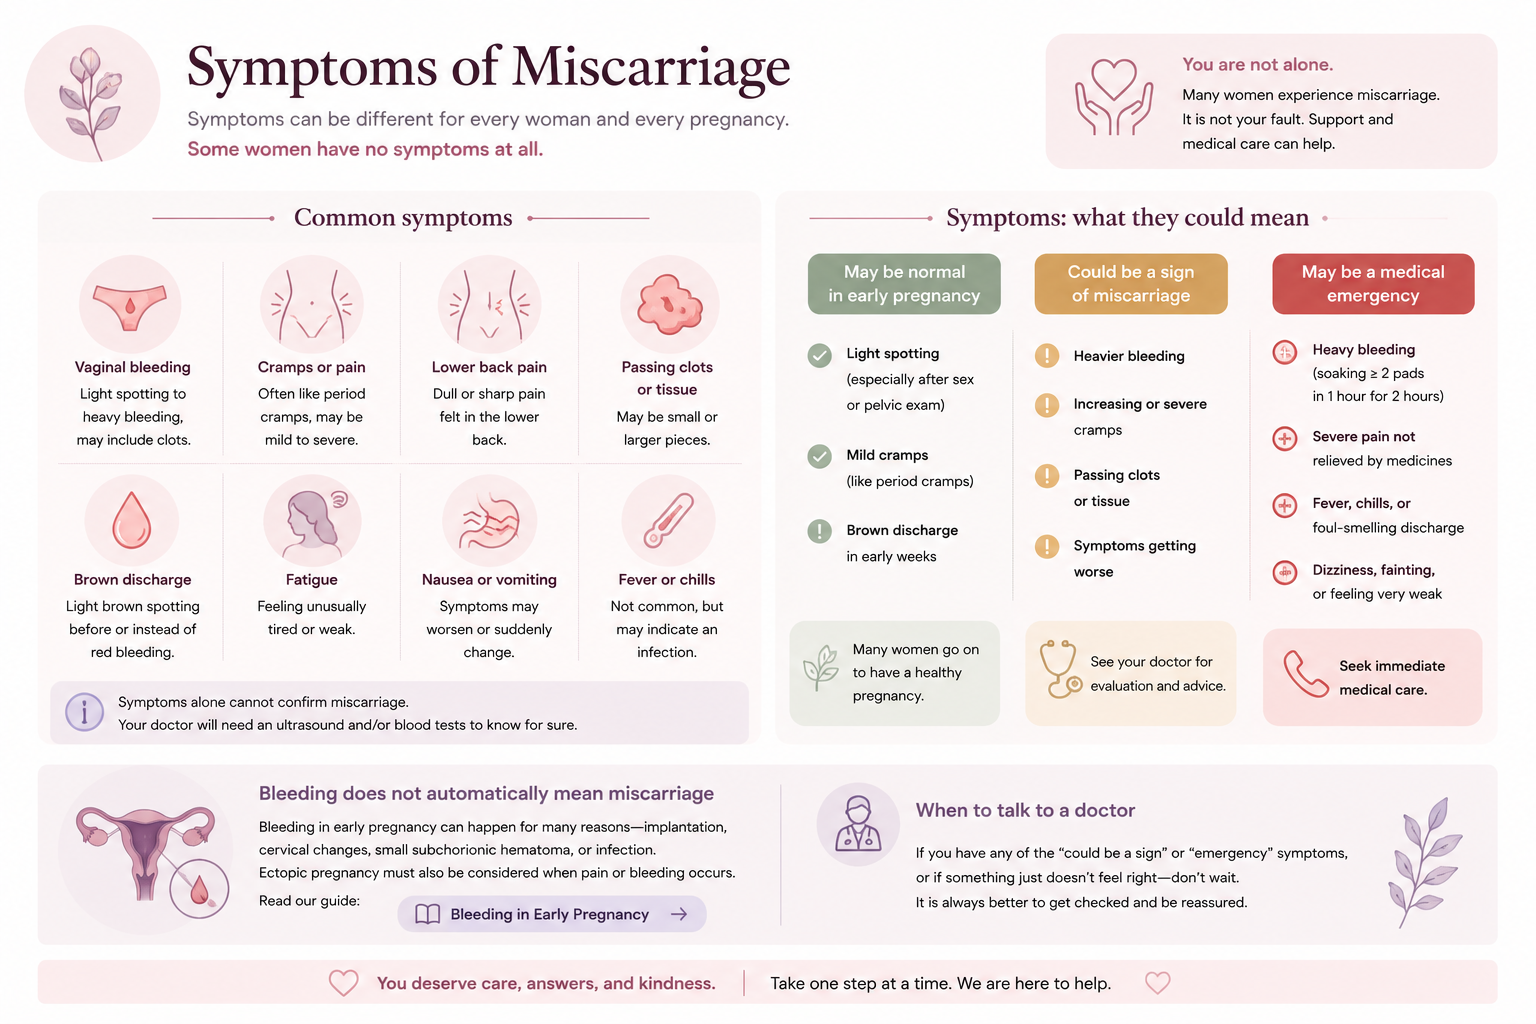
Common symptoms can include
- vaginal spotting or bleeding
- bleeding that becomes heavier
- lower abdominal or pelvic cramps
- lower back discomfort
- passing clots or pregnancy tissue
- a reduction in pregnancy symptoms in some women
Bleeding does not automatically mean miscarriage
Light spotting and even some episodes of bleeding can occur in pregnancies that continue normally.
Bleeding should therefore be assessed in context rather than used by itself to diagnose pregnancy loss.
Read our guide to Bleeding in Early Pregnancy for the other possible causes and the symptoms that need urgent care.
How do doctors know whether a miscarriage has occurred?
This is one of the most important parts of early-pregnancy care because a miscarriage should not be diagnosed simply because a pregnancy appears smaller than expected on one very early scan.
Ovulation may have occurred later than expected, menstrual dates may be uncertain, or the pregnancy may simply be earlier than calculated.
Ultrasound
A transvaginal ultrasound can assess the pregnancy sac, yolk sac, embryo and fetal heart activity depending on how far the pregnancy has developed.
Pregnancy dates
Your last menstrual period can help estimate gestation, but dates alone cannot prove whether a pregnancy is viable.
Beta-hCG
Blood beta-hCG measurements may be useful when ultrasound findings are not yet conclusive, particularly when measurements are repeated.
Repeat assessment
If the pregnancy is simply too early to judge safely, another ultrasound after an appropriate interval may be needed before making a final diagnosis.
Waiting for another scan can be emotionally difficult, but when the findings are uncertain it can prevent a healthy but earlier-than-expected pregnancy from being mistakenly diagnosed as a pregnancy loss.
Treatment to empty the uterus should generally begin only after the diagnosis is sufficiently certain, except when urgent treatment is required because of the woman’s clinical condition.
Different ways miscarriage can present
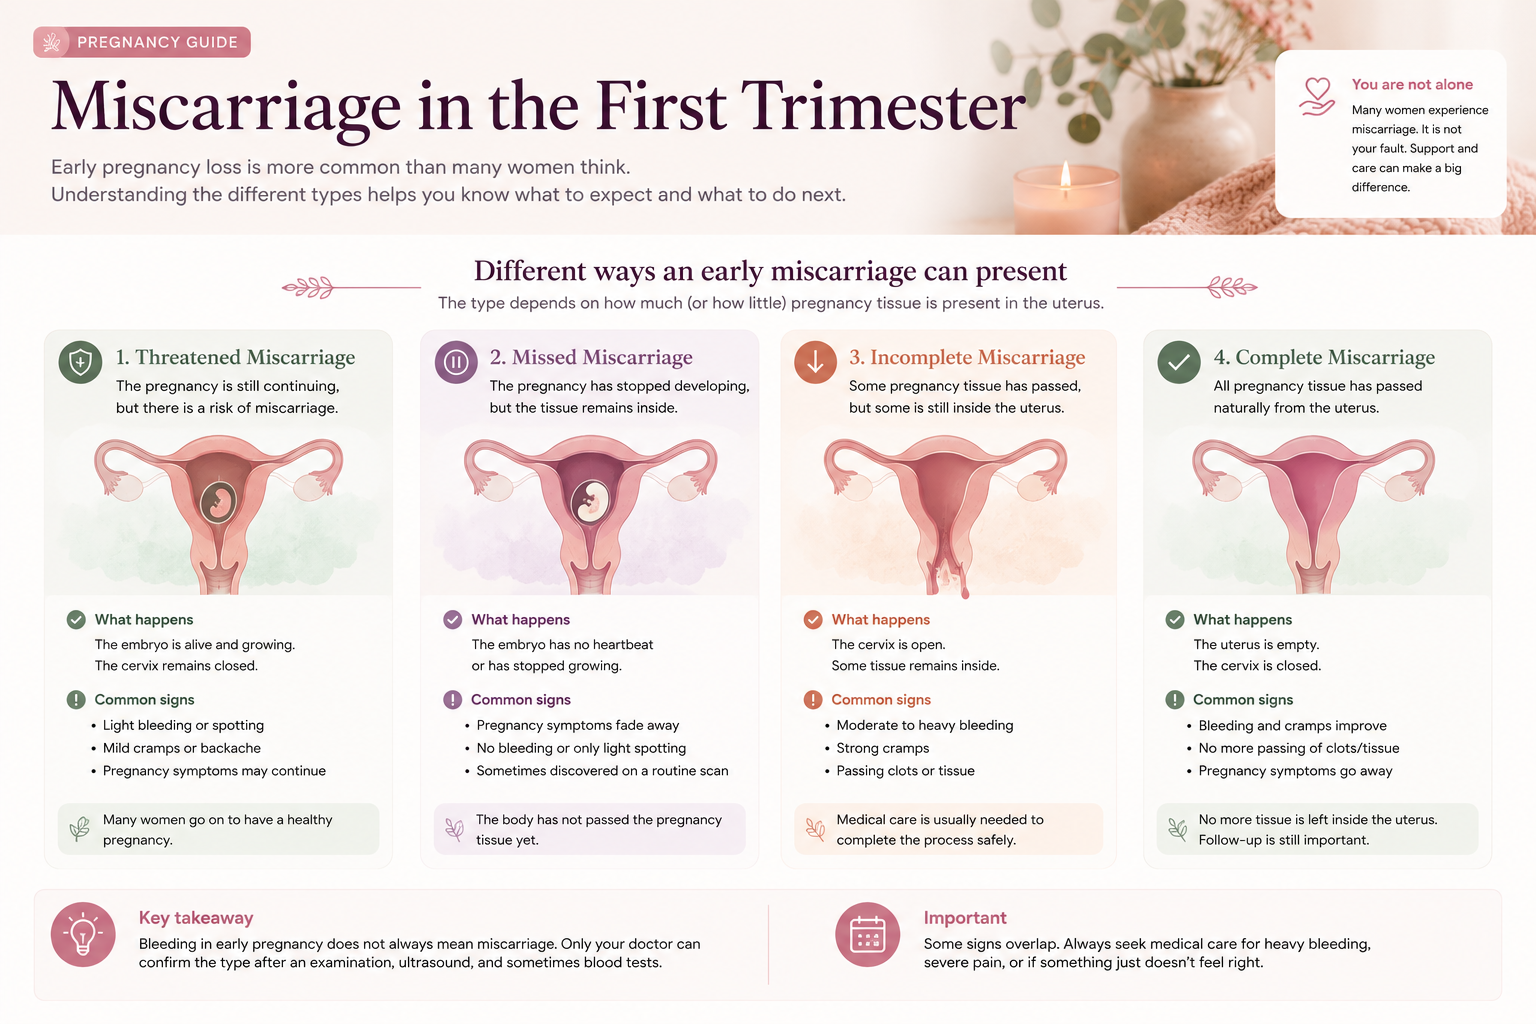
You may hear doctors use terms such as threatened, missed, incomplete or complete miscarriage. These words describe what appears to be happening clinically and on ultrasound.
Threatened miscarriage
There is bleeding during pregnancy, but the pregnancy may still be developing normally. If ultrasound shows an intrauterine pregnancy with fetal heart activity, this is not a confirmed pregnancy loss.
Depending on the woman’s history and local clinical guidelines, progesterone may sometimes be prescribed for selected women who have early pregnancy bleeding and previous miscarriage.
Missed miscarriage
The pregnancy has stopped developing, but the body has not yet passed the pregnancy tissue. There may be little bleeding or pain, and the diagnosis is often made on ultrasound.
Incomplete miscarriage
Some pregnancy tissue has passed, but some remains inside the uterus. Bleeding and cramping may continue until the uterus is empty.
Complete miscarriage
The pregnancy tissue has passed and the uterus is empty. If this has been confirmed and the woman is clinically well, further treatment to empty the uterus is usually not required.
What happens after miscarriage is confirmed?
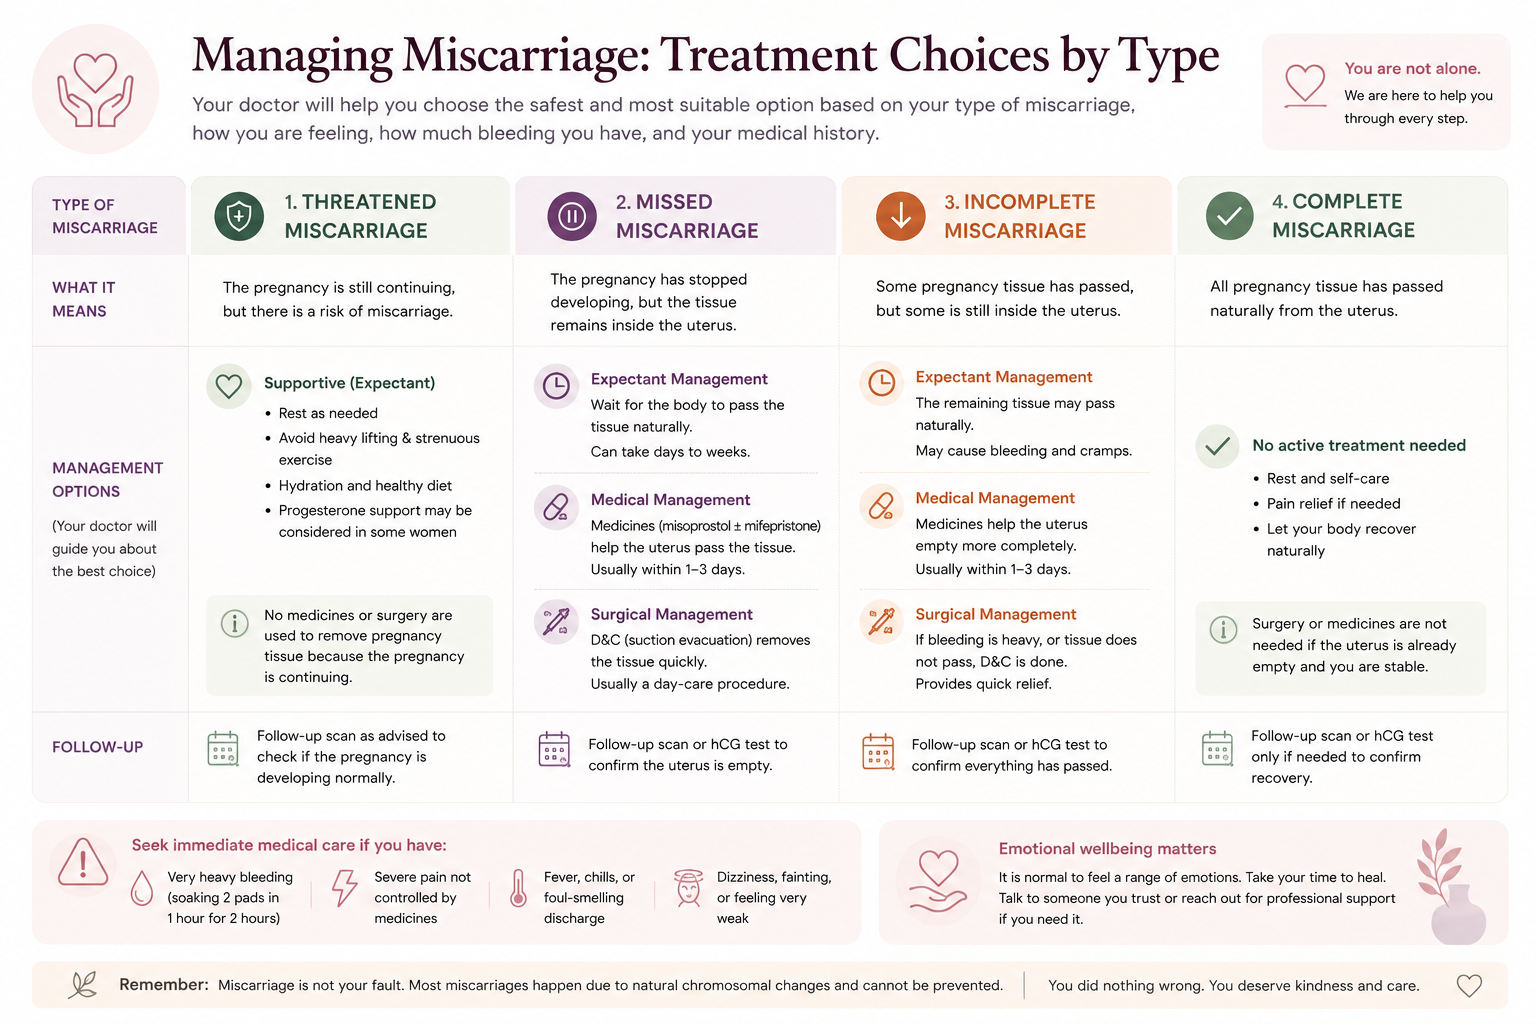
There is not one treatment that is best for every woman. When a miscarriage has been confirmed and there is no emergency, the main options are waiting for the pregnancy tissue to pass naturally, using medicines, or surgical treatment.
The safest choice depends on the type of miscarriage, bleeding, infection, ultrasound findings, other medical conditions and — importantly — the woman’s own preference.
1. Expectant management — waiting naturally
If you are medically stable, you may choose to wait for the uterus to pass the pregnancy tissue naturally.
Bleeding and cramping can become stronger when the tissue passes. Follow-up is important to make sure the miscarriage has completed. If tissue remains, another period of waiting, medicine or surgery may be discussed.
2. Medical management — using medicine
Medicines can be used to encourage the uterus to contract and expel the pregnancy tissue. Misoprostol is commonly used, and some protocols use mifepristone before misoprostol for certain types of early pregnancy loss.
Cramping, bleeding and passage of clots or tissue are expected as the medicine works. Your doctor should explain what amount of bleeding to expect, which pain relief can be used and when urgent medical assessment is needed.
3. Surgical management
Surgical evacuation removes pregnancy tissue through the cervix. It is the fastest and most predictable way to empty the uterus and may be chosen because of clinical circumstances or simply because the woman prefers this option.
Surgery becomes particularly important when there is heavy ongoing bleeding, haemodynamic instability, suspected infection, or when other treatment has not successfully emptied the uterus.
What actually happens during a D&C?
Women are often told they may need a “D&C” after miscarriage. Here is what that usually means in modern early-pregnancy care.
D&C means dilation and curettage. However, for first-trimester miscarriage, pregnancy tissue is now commonly removed using suction or vacuum aspiration rather than relying on sharp scraping of the inside of the uterus.
You may therefore hear several terms used, including D&C, suction evacuation, surgical evacuation, vacuum aspiration or MVA (manual vacuum aspiration).
Your medical team confirms the diagnosis, reviews your bleeding and medical history, and explains the procedure. Medicine may be given beforehand to soften or prepare the cervix.
Depending on the procedure and hospital, this may involve local anaesthetic, sedation or general anaesthesia.
The cervix is the opening between the vagina and uterus. It may be gently dilated enough to allow the suction instrument to pass.
The clinician passes a narrow tube through the cervix and uses suction to remove the remaining pregnancy tissue from inside the uterus.
Once the uterus has been emptied and bleeding is controlled, you are monitored during recovery. Many women can return home the same day when medically stable.
When might surgery be recommended?
- heavy or persistent bleeding
- signs of infection
- retained pregnancy tissue
- expectant or medical management has not worked
- a faster, more predictable treatment is preferred
- your clinical condition makes waiting less appropriate
What might I feel afterward?
Cramping and vaginal bleeding or spotting can occur after the procedure. Your healthcare team will explain pain relief, follow-up and when you can return to normal activities.
Are there risks?
Surgical management is generally safe. Possible complications include infection, heavy bleeding, retained tissue requiring another procedure and, less commonly, injury or perforation of the uterus. Intrauterine scar tissue or adhesions can occur but are uncommon.
Why does miscarriage happen?
In many first-trimester miscarriages, the pregnancy stopped developing because of a chromosome problem that occurred during early development. These abnormalities usually happen by chance.
They are not caused by ordinary activities such as walking, climbing stairs, working, travelling or having a normal argument.
Sometimes other medical factors are relevant, particularly after recurrent pregnancy losses, but after one early miscarriage an exact cause often cannot be identified.
What should you expect after miscarriage?
Physical recovery depends on how the miscarriage occurred and which treatment was used. Bleeding usually becomes lighter with time and cramping should gradually improve.
Your healthcare team may use symptoms, a pregnancy test, ultrasound or beta-hCG follow-up depending on your situation to confirm that the pregnancy tissue has passed.
Some women feel intense grief. Others feel numb, angry, relieved, confused or experience several emotions at once. There is no single “correct” emotional response to pregnancy loss.
Partners may also experience grief differently. Support from someone you trust, your doctor or a mental-health professional can be helpful if the loss is becoming difficult to cope with.
Can I have a healthy pregnancy after miscarriage?
Yes. A single first-trimester miscarriage usually does not mean that you will be unable to have a successful future pregnancy.
Ovulation can return before your next menstrual period, so pregnancy can occur again relatively quickly.
When to try again is partly a medical decision and partly a personal one. You may be physically ready before you feel emotionally ready. Your doctor can advise you if there was infection, heavy bleeding, surgery, molar pregnancy, an ectopic pregnancy concern or another reason to delay.
Planning another pregnancy?
Continue or restart folic acid before conception unless your doctor has advised a different dose, review important medicines and health conditions, and seek medical advice early when you next have a positive pregnancy test if additional monitoring has been recommended.
Seek urgent medical care if you have
- very heavy or rapidly increasing vaginal bleeding
- severe or worsening abdominal or pelvic pain
- severe one-sided abdominal pain
- shoulder-tip pain
- dizziness, fainting, marked weakness or collapse
- fever, chills or feeling very unwell
- foul-smelling vaginal discharge
- significant bleeding together with symptoms of faintness
Severe one-sided pain, shoulder pain, dizziness or collapse can also occur with a ruptured ectopic pregnancy, which can cause internal bleeding and requires emergency assessment.
Frequently asked questions
Does bleeding always mean I am miscarrying?
No. Bleeding can occur in a continuing pregnancy. Ultrasound and clinical assessment are often needed to determine the cause.
Can a miscarriage happen without bleeding?
Yes. A missed miscarriage may cause little or no bleeding and can be discovered during a routine ultrasound.
Can one early ultrasound confirm miscarriage?
Sometimes the findings are definitive, but not always. If the pregnancy is very early or measurements are uncertain, another ultrasound after an appropriate interval may be needed before confirming pregnancy loss.
Do I always need a D&C?
No. Many clinically stable women can choose expectant or medical management. Surgery may be recommended for heavy bleeding, infection, retained tissue, unsuccessful other treatment, or chosen because the woman prefers a faster and more predictable option.
Will miscarriage affect my ability to become pregnant again?
Most women who experience one early miscarriage can later have a successful pregnancy. Additional evaluation may be considered when pregnancy losses recur or when the clinical history suggests another medical problem.
When will my pregnancy test become negative?
Pregnancy hormone levels do not disappear immediately after a pregnancy ends, so a home pregnancy test may remain positive for some time. Follow the testing or follow-up plan given by your healthcare team.
My Pregnancy
See pregnancy information organised around where you are in your pregnancy and what comes next.
Open My PregnancyAsk a Doctor for Free
Have a question about bleeding, ultrasound results, beta-hCG or what your doctor has told you? Send your question to the AuratSehat team.
Ask a DoctorRelated Pregnancy guides
Medical references
- American College of Obstetricians and Gynecologists (ACOG). Early Pregnancy Loss. Practice Bulletin No. 200.
- National Institute for Health and Care Excellence (NICE). Ectopic pregnancy and miscarriage: diagnosis and initial management (NG126).
- Royal College of Obstetricians and Gynaecologists (RCOG). Early miscarriage.
- Royal College of Obstetricians and Gynaecologists (RCOG). Recovering from surgical management of a miscarriage.
AuratSehat medical guides are written for patient education and do not replace individual medical assessment. Pregnancy bleeding, pain and suspected pregnancy loss should be evaluated according to your symptoms, gestational age, examination, ultrasound findings and other relevant investigations.